
The formal notification of the United States’ intent to withdraw from the World Health Organization (WHO) represents a significant geopolitical shift in global public health governance. This decision, which reverberated across international health corridors, challenges the established framework of multilateral cooperation that has defined post-World War II diplomacy. As the world remains locked in complex battles against both emerging pathogens and entrenched diseases, the potential departure of the WHO’s largest single-state donor creates a vacuum in funding, technical leadership, and collaborative infrastructure.
A Historical Foundation of Cooperation
To understand the gravity of the current situation, one must look back to the inception of the World Health Organization. Established on April 7, 1948, the WHO was envisioned as the specialized agency of the United Nations responsible for international public health. The United States was not merely a signatory to the WHO Constitution; it was a primary architect. For over seven decades, the synergy between the U.S. Centers for Disease Control and Prevention (CDC), the National Institutes of Health (NIH), and the WHO has been the bedrock of global health security.
This partnership has yielded monumental victories in human history. The global eradication of smallpox, declared in 1980, remains the gold standard for what international cooperation can achieve. Furthermore, the Global Polio Eradication Initiative, which brought polio cases down by more than 99% since 1988, stands as a testament to the persistent, combined efforts of American scientific expertise and the WHO’s operational reach.
Chronology of the Relationship and Recent Tensions
The relationship between the United States and the WHO has historically been robust, though not without periods of intense scrutiny.
- 1948: The United States officially joins the WHO, becoming a cornerstone member.
- 1950s–1970s: The U.S. plays a leadership role in the global campaign to eradicate smallpox, providing both financial resources and logistical support.
- 2014–2016: The WHO faces global criticism for its slow response to the Ebola epidemic in West Africa. This period prompts significant internal debates regarding the organization’s capacity for rapid intervention.
- 2017–2020: The WHO undergoes a rigorous internal reform process, focusing on accountability, transparency, and fiscal efficiency to address criticisms from member states, including the United States.
- 2020: The announcement of the U.S. intent to withdraw marks the most significant diplomatic rift in the organization’s history, citing disagreements over transparency and institutional governance.
Supporting Data: The Scale of U.S. Contribution
The financial implications of a U.S. withdrawal are profound. Historically, the United States has contributed hundreds of millions of dollars annually to the WHO, covering both assessed contributions—the mandatory dues based on wealth and population—and voluntary contributions, which are earmarked for specific programs such as polio eradication, vaccine-preventable diseases, and emergency response.
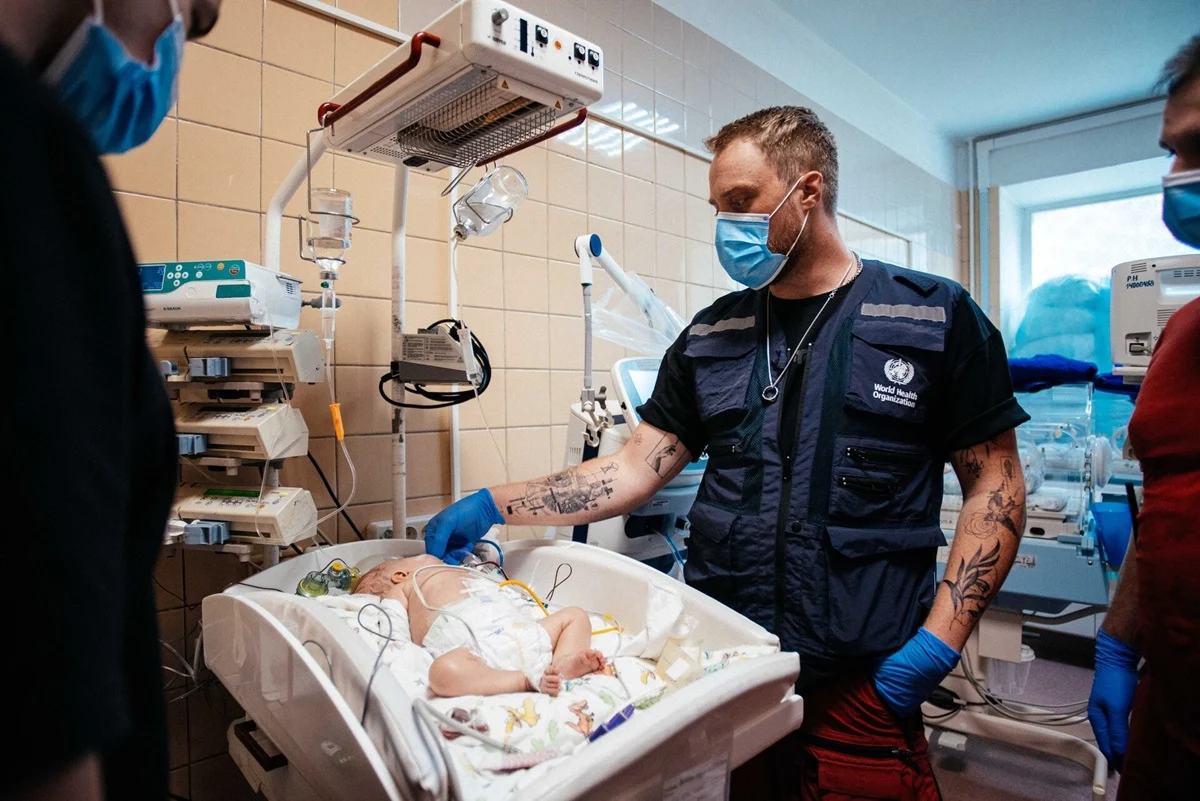
Data from the WHO financial records indicate that U.S. voluntary contributions have often exceeded $400 million per year. These funds are vital for operations in high-risk zones, including conflict-ridden areas where the WHO acts as a provider of last resort. Without this sustained financial injection, the organization faces a potential budgetary crisis that could derail ongoing field operations in regions such as the Sahel, the Horn of Africa, and conflict-affected Ukraine, where the WHO continues to facilitate medical evacuations and critical care for vulnerable populations.
Perspectives from the Global Health Community
The international response to the proposed withdrawal has been characterized by widespread concern from public health experts, academic institutions, and foreign governments. Organizations such as the American Public Health Association (APHA) and the Council on Foreign Relations have highlighted that a withdrawal would not only harm the WHO but would also limit American access to real-time data on global health threats.
"The WHO serves as the world’s early warning system," noted one senior public health analyst familiar with the organization’s operations. "When the United States withdraws from that ecosystem, it effectively blinds itself to the intelligence-sharing networks that allow the CDC to track the movement of dangerous pathogens across borders."
Furthermore, from a diplomatic standpoint, European and Asian allies have expressed that the absence of the U.S. seat at the table could lead to an increase in the influence of other geopolitical powers within the organization’s governing bodies, potentially shifting the focus of global health policy away from the standards traditionally advocated by Western nations.
Implications for Global Health Security
The withdrawal of the United States poses a multi-faceted risk to global health security. Firstly, the WHO’s ability to coordinate large-scale responses to pandemics depends heavily on the legitimacy afforded by universal membership. When a founding member exits, the organization’s political leverage is weakened, making it more difficult to enforce international health regulations—the legally binding instrument that mandates countries to report and respond to health emergencies.
Secondly, the technical collaboration between American researchers and WHO-affiliated laboratories is extensive. The WHO’s network of Collaborating Centres, many of which are based in American universities and federal research institutes, ensures that the latest medical innovations are shared globally. A withdrawal creates bureaucratic hurdles that could impede the seamless exchange of scientific data, potentially delaying the development of vaccines, therapeutics, and diagnostics during future outbreaks.
Looking Toward Reconciliation
Despite the formal notification of withdrawal, the WHO leadership has maintained a posture of openness, emphasizing the importance of constructive dialogue. In its official communications, the organization has underscored the reforms implemented over the last seven years, noting that the WHO of today is more transparent and accountable than it has been in decades.
The WHO’s plea for the United States to reconsider is not merely a request for funding; it is an appeal for the preservation of a system that protects the health of the American public by addressing threats before they reach domestic shores. The argument remains that the health of the global population is interconnected; in an era of rapid international travel and migration, the containment of infectious disease at its source is the most effective form of national health security.
As the international community watches these developments unfold, the focus remains on whether a path for re-engagement can be established. The "constructive dialogue" requested by the WHO leadership is viewed by many as the only viable mechanism to address the grievances of the United States while maintaining the integrity of a global health architecture that has served as a safeguard for humanity for over seventy years.
In conclusion, the potential departure of the United States represents a critical juncture for the World Health Organization. It forces a reckoning not only with the organization’s governance and reform efforts but also with the fundamental question of whether global health is a shared responsibility that transcends national borders. As the dialogue continues, the health and well-being of millions, from the remote clinics of rural Africa to the medical centers of North America, remain at the heart of the debate. The legacy of seven decades of collaboration serves as a reminder of the fragility of international health systems and the imperative of maintaining the alliances that keep the world safe from the next silent, microscopic threat.
