
A Legacy of Cooperation: The Historical Context
The relationship between the United States and the World Health Organization (WHO) dates back to the organization’s inception. Following the devastation of World War II, the United States played a primary role in the 1948 establishment of the WHO, viewing global health as a cornerstone of international stability and national security. For over seventy years, this alliance has been central to the eradication of smallpox—a milestone achieved in 1980—and the near-total elimination of polio, which has seen cases drop by more than 99% since the Global Polio Eradication Initiative was launched in 1988.
Throughout the late 20th and early 21st centuries, the U.S. served not only as the largest individual donor to the WHO but also as a primary source of technical expertise. American institutions, including the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH), have long maintained close collaborative ties with the WHO. These partnerships have been instrumental in managing outbreaks ranging from HIV/AIDS and Ebola to the influenza pandemics that have historically threatened global supply chains and economic stability.
Chronology of the Withdrawal Process
The decision to withdraw follows a period of heightened scrutiny regarding the WHO’s administrative processes and its operational response to global health crises. While the formal notice of withdrawal signifies the intent to depart, the process is not instantaneous. Under the terms of the WHO constitution, a member state must provide one year’s notice and meet all outstanding financial obligations to complete the withdrawal process.
This window of one year serves as a critical cooling-off period. Diplomatic observers note that this duration provides an opportunity for continued negotiations, technical discussions, and the potential for a reversal of policy. The timeline for this process involves a complex series of administrative reviews, congressional deliberations within the United States, and intense back-channel negotiations between the U.S. Department of State and the WHO’s leadership in Geneva.
Financial and Operational Impact: Supporting Data
The financial implications of a U.S. departure are profound. The United States typically provides a significant portion of the WHO’s total budget, encompassing both assessed contributions—the mandatory dues based on a country’s wealth and population—and voluntary contributions directed toward specific programs, such as maternal health, vaccine distribution, and emergency preparedness.
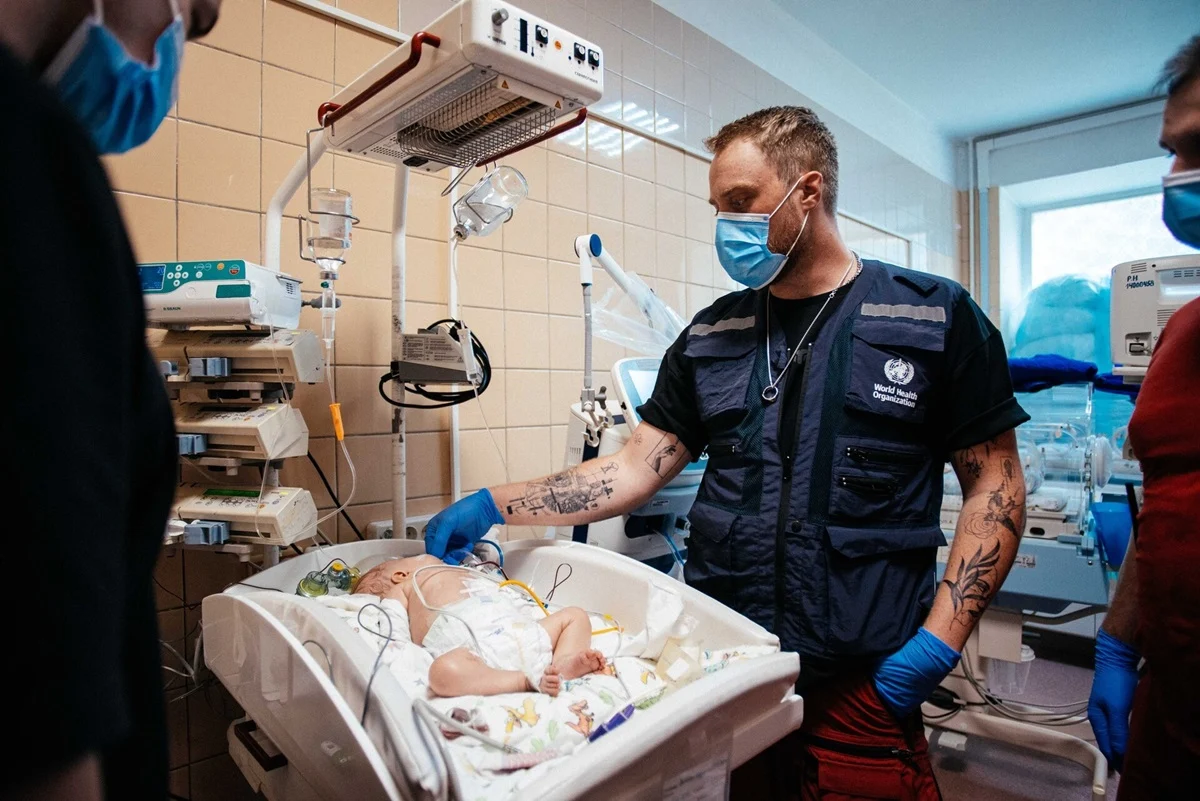
Data from the WHO’s financial statements indicate that the loss of U.S. funding would create a massive budgetary shortfall. Beyond the immediate fiscal impact, the operational consequences could be severe. The WHO relies on U.S. institutional support to coordinate global response teams, manage laboratory networks, and deploy health workers to conflict zones, such as the ongoing efforts to facilitate medical transfers for patients in Ukraine and other regions of instability. Without the logistical and financial backing of the U.S., the WHO’s capacity to perform surveillance on emerging pathogens and coordinate global vaccine rollouts would be significantly diminished.
Institutional Reforms and Accountability
Over the past seven years, the WHO has undergone what is described as the largest set of reforms in its history. These changes were initiated to address long-standing criticisms regarding the organization’s agility, cost-effectiveness, and transparency. Key areas of reform have included:
- The WHO Health Emergencies Programme: Established to provide a more rapid and robust response to health crises, ensuring that the organization can deploy resources within hours rather than weeks.
- Accountability Frameworks: The implementation of stricter oversight mechanisms to ensure that donor funds are tracked and utilized with maximum efficiency.
- Governance Modernization: Efforts to streamline the World Health Assembly and Executive Board processes, ensuring that member states have more direct oversight of the WHO’s strategic priorities.
Despite these efforts, the U.S. has maintained that structural issues persist. The tension between the need for an independent, science-based global body and the sovereign interests of individual member states remains a central friction point. The WHO maintains that its reforms have already resulted in measurable improvements, citing increased impact in field operations and better coordination with local health ministries in low-income nations.
Global Reactions and Diplomatic Perspectives
The international community has reacted with varying degrees of concern. Leaders from European, Asian, and African nations have expressed alarm, warning that the withdrawal of a superpower from the global health architecture could lead to a "fragmentation of effort." Health experts argue that infectious diseases do not recognize national borders, and that the withdrawal of the U.S. could embolden other nations to scale back their own commitments, potentially weakening the global "immune system" that the WHO represents.
Public health advocates and NGO representatives have highlighted that the individuals most affected by a withdrawal would be those in the most vulnerable regions of the world. By losing access to the WHO’s coordinated efforts, developing nations may struggle to maintain vaccination schedules for childhood diseases, manage chronic condition treatments, and handle localized outbreaks before they become regional pandemics.
Analysis: The Future of Global Health Security
The potential exit of the United States from the WHO raises fundamental questions about the future of international cooperation. In an interconnected global economy, health security is inextricably linked to economic prosperity. When outbreaks occur, the speed and accuracy of the WHO’s data-sharing protocols are the primary defense against the economic disruption caused by trade bans and travel restrictions.
If the withdrawal proceeds, the global health landscape will likely shift toward more regionalized or bilateral health agreements. While some argue that this could lead to more nimble, specialized partnerships, critics contend that it would erode the universal standards and norms that the WHO has established over decades. The WHO’s unique ability to act as a neutral arbiter in health data—gathering information from countries even during times of political tension—is a function that would be difficult for any single nation or smaller coalition to replicate.
Conclusion and Path Forward
The World Health Organization has officially expressed its hope that the United States will reconsider its position. The leadership in Geneva emphasizes that the partnership between the U.S. and the WHO has historically saved countless lives and remains essential for the protection of global health.
As the one-year notice period progresses, the global community remains in a state of watchful waiting. The focus for the coming months will likely center on whether constructive dialogue can address the concerns raised by the United States while preserving the integrity and mandate of the WHO. The outcome of these discussions will not only define the relationship between a single nation and a global agency but will also set a precedent for how the international community navigates health security in the 21st century.
The health and well-being of millions of people worldwide hinge on the ability of global powers to prioritize collective safety over individual political disputes. Whether the U.S. remains within the fold or pivots toward a new model of global health engagement remains the most pressing question for the international diplomatic and medical communities. For now, the WHO continues its work, maintaining its focus on the ground, where the reality of disease and the need for global solidarity remain constant and urgent.
